shutterstock 526175119 1

‘The role of exercise post-op and why it is important for a healthy life’ by Luke Hart

Watch this video of Luke Hart, Senior Strength & Conditioning Coach and Fitness Lab Lead at UPMC Sports Surgery Clinic, presenting on ‘The role of exercise post-op and why it is important for a healthy life’.

This presentation was recorded as part of SSC’s Public Information Meeting focusing on Orthopaedics in March 2021.

Luke HartLuke Hart is a Senior Strength & Conditioning coach at UPMC Sports Surgery Clinic.

Luke Leads SSC’s Fitness Lab and Health Lab Programmes in our state of the art Sports & Exercise Medicine Department.

Thank you very much. So, tonight I’m going to present on the role of exercise postoperatively, and why it’s important for us to do them to lead a healthy and fit life.

Exercise really is critical to pre and post on exercise and fitness – preoperatively it’s really important to make sure that you build strength, so that post-op, you find you can get that strength back a little bit easier and we’ll go through why that is, but also for you leading a fit and healthy lifestyle postoperatively and I’ll show some details tonight, why that’s so important and why a lot of people do struggle to keep their fitness and health up after operations.

And so, an important fact to look at tonight is the fact that as we get older, the more important it is for us to stay strong and stay healthy.

Because as we get older, we start to drop off more and more in these qualities, and therefore it’s easier for us to lose strength quicker if we’re not using our muscles.

And after post-ops or after an operation, it’s obviously a period of where we’re not using those muscles and as we get older, we’ll lose them quicker. The old adverb ‘if we don’t use it we lose it’ definitely fits into this scenario, and so it’s a really important component that we’re going to talk through tonight.

So first off, why is it important and why is strength important currently?

Well, you can see here on the top left, we can see a 60-year-old woman with muscle mass – the dark part there is the muscle and the white part is the fat.

Then on the right-hand side, we can see an eighty-year-old woman with the dark part and the fat and we can see that that fat is starting to infiltrate into the muscle, so we can see more fat within the muscle and more fat around the muscle.

When we’re not using our muscle this is essentially what happens to it so after an operation, especially a lower limb operation, this is what will happen when we’re not using those muscles.

We can see on the graph below that as we age, as we kind of get to around about 30, we can start to see that decline in the muscles, what we call cross-sectional area, the amount of muscle that we have.

What that depicts is the amount of non-contractile elements to that muscle so that’s the fat, the adipose tissue the collagen, things that don’t help us in our day to day lives going up and down the stairs, standing up from a chair, etc.

Unfortunately, as I said, as we age we lose this.

Having said that, we can do a lot to make sure that we don’t lose it, or we’ve stifled the amount that we’re losing it by. And this has been showing up across the board and in cross populations. So even people who are even in hospital, have been shown to really improve their cross-sectional area, their strength and their function, and even people in care homes have been shown to short to 80% improvement in muscular strength when they start a strength training program.

So really is for everybody, not just for young fit and healthy people. And so it doesn’t have to be the case that we’ve seen this big drop off.

So it’s absolutely reversible and what we can see here is a picture that was done by a study called Wroblewski in 2011 that shows a 40-year-old triathlete at the top there. You can see the great muscle quality that he has with the slight little bit of fat around the outside.

We can then see a 74-year-old sedentary man who’s not doing much exercise below that. And what you can see there is that the fat around the muscle is much larger but the fat running through the muscle is also a much higher percentage.

And then at the bottom, we can see a 70-year-old triathlete. So we can see that the 70-year-old triathlete looks much the same as the 40-year-old triathlete, maybe not even better, and while he may not be as strong, or as fast his muscle quality is still just as good. And so it’s absolutely available for everybody to improve to this level, and it’s really important that we understand that.

But then why is strength itself so important?

Well, strength has a really strong correlation with mortality – the stronger we are, the less likely we are of essentially passing away or dying and so we can see that in big population cohorts – stronger people tend to live longer, tend to live healthier lifestyles and tend to do the things they love for longer.

So if we’re stronger, we tend to walk for longer we tend to play tennis for a few extra years, golf for a few extra years. So it’s really important that we make sure we maintain our strength. And strength has been shown to correlate with reduced risk in nearly every category, including cardiovascular disease and in terms of risk of mortality.

So it’s really important that we stay strong.

Lots of studies have shown that if we can keep the whole body strong, not just the upper body or not just the lower body but the total body is what’s really important to having a whole body workout – something that strengthens all the different regions of your body is really important.

But also, it reduces the risk of falls, and obviously subsequent fractures so after post-op, obviously that’s a slight risk is that we don’t have the strength and we don’t have the capabilities and function to move properly, then we’re going to be at higher risk after post-op.

If we now kind of know that strength is really important and strength postoperatively is really important, you’re going to lose muscle mass on that one side, and we may lose function if we’re not really careful.

How is the best way to go about getting that strength back?

Well in this study they looked at people who did no exercise, endurance exercise, and then strengthening resistance training exercise.

What we can see is that the strengthening and resistance training with endurance had the best results.

So we can see that the top one there in green, had the best percentage improvement over 10 and 21 weeks and we can see nearly a 20% improvement in that group over 20 weeks, which is fantastic – percentage improvement, every single week when you’re doing some form of strength, endurance training, which is fantastic. And we can see that in both the lower body and in the upper body which is really important as well.

And then when we look at certain conditions we see that strength training is really important. Knee OA is probably one of the most prevailing, and we can see here that if we do some strength training with anybody who has knee osteoarthritis, which is a lot of people that have a knee replacement, we see that resistance training positively correlated with significant improvements in people’s function.

So people self-reported function the amount of walking they could do, stairs, hills going up and down hills massively improved with strength.

One of the common complaints that we have here is that people really struggle going up and downhill. Well, that is one of the key ones where strength will massively help you. So if you are stronger you will find it much easier coming downhill, than if you’re not strong, and that’s because when we go downhill we start to compress the joint we load the joint more going downhill, so we need to be stronger to deal with those forces.

We also saw decreases in pain as well as we get stronger and a 17.5% improvement in function.

Then the second study that was done on 500 people showed improved quadriceps strength actually improve people’s walking. That’s really important because a lot of people here struggle with their walking and actually pain may be secondary to the fact that they’re struggling with function. And if they’re struggling walking and going to the shops, strength is really the biggest port of call.

So if function is your problem and you’re finding it in the pain isn’t the biggest issue, that function is the issue that that’s where we can really help, and that’s where we can step in and get a strength program for you.

Strength also helps you to stop offloading onto the other leg. So sometimes what we see is if we start to get sore on one side, we offload onto the other leg and that’s how I get sore and that’s why strengthening is really important to make sure that doesn’t happen for you.

In a big meta-analysis of 2 million people it’s found that actually making sure your whole body was really strong was the biggest sort of way of reducing your risk of mortality, and actually was very comparable to actually just doing cardiovascular exercise, and obviously, we all know how important it is to do cardiovascular exercise, and we’ll touch on that in a minute, but not many people focus on strength.

So there are some very positive effects of strength training pre-operatively, especially in hip replacements.  In hip replacements it’s found that pre-op strength training – so doing a good bit of strength before you go into the operation, significantly improved your function post-operation, and people who had done pre-op strengthening got back quicker after the operation.

So it’s a really good incentive if you’re thinking about a hip replacement at any point in the future, there are massive benefits to doing some strength training beforehand.

We found that pre-op quadriceps exercises and pre-op quadricep strength – so the muscle on the front of your thigh has a significant correlation with our post ACL quadriceps strength as well. So if you heard it before, it’s likely you’ll get it afterwards. But maybe it’s not so easy if you don’t have it before.

Then there were significant effects, one year postoperatively for those people who had knee replacements, especially when they were stronger.

So they were stronger had better post-op results at one year post and those that didn’t know didn’t have that strength. So it’s very, very important and there are lots of reasons why we should make sure we’re doing some form of strength, once or twice a week.

WHO Guidelines for maintaining healthy lifestyle

That brings me on to why the World Health Organization, approximately a couple of years ago changed their guidance and what they said was actually everyone was doing the cardiovascular side of things, but actually, we need strength in that and they recognize that without strength we can’t do the cardiovascular exercise because maybe we’re too sore, or maybe we have too much pain or we lose function.

So, what they’ve now suggested is that we do strength training twice per week.

And so they put out and this is the UK version – very, very similar to the World Health Organization, where they put out that two strength sessions a week, should be done for everybody to lead a healthy lifestyle.

Okay, and alongside that you’ll see a few other bits you’ll see 150 minutes of light, physical activity or 75 minutes of vigorous physical activity, some form of balanced training, and then to try and minimise, how much time you spend doing nothing, or just resting and trying to make sure we need just a generally healthy lifestyle.

That’s really important because obviously, we know how important our steps are our daily steps. We know that roughly we should be getting around about 7000 daily steps. Anything above that in the research seems to be not too much but doesn’t make as much benefit. But after 7000 steps it seems to be intensity is more important so make sure you’re doing intense steps or getting the heart rate up a bit higher seems to be more important 7000, is that is the amount that we want.

And so we can see that this is really important for managing stress, our weight, our mood and our sleep, which all have really important consequences, but also we can see there at the top on the right-hand side type two diabetes, cardiovascular disease, falls, depression, joint & back pain, and even cancer.

Cardiovascular Fitness

So we know it’s important to be strong. We’ve kind of gone through that and we’ve hashed that one out but now we want to have a look at cardiovascular fitness.

This has been very well documented but I just wanted to go through a couple of points, so we can see here that this is a study that looks at your V02 max – that’s the amount of oxygen you can use and is commonly used to kind of guide how fit you are, tell us how fit you are.

And we want to know how many mil’s of oxygen you can use per kilo of your body weight. And we can see the top category people that can use 37.1 mils per kilo – that is the lowest amount they can score, have the least number of deaths versus, people who are under maybe 27 had the highest amount of deaths.

So even a very small improvement in your V02 Max, aka your fitness can have massive effects on your risk.

Whether it’s a choice of you know maybe going out for a walk or maybe going for a little bit of extra exercise, we should always choose that option. No amount, however small it is, is a bad option.

And that’s why it’s really important why postoperatively, we get our strength back – If we get our strength back, we can start to do some cardiovascular fitness. And that’s also why, if maybe we have an ACL or we have a knee replacement, we should try and get back to maybe some arm bike or we should get back to swimming as quickly as we can, or back to cycling – finding an option that works for you, allows you to raise the heart rate and work on that cardiovascular fitness.

We would guide most of our patients here to be doing one low-intensity cardiovascular session a week. So it could be a long walk, it can be a very gentle cycle. It’s just something that takes the heart rate up a couple of per cent, maybe to around about 90 to 110 beats per minute but it’s individual for everyone.

One at medium intensity, so this could be a sport, it could be you know an easy sport: golf is a perfect example where we’re walking quite quickly. Then one high-intensity session – some examples of this that we use with all of our post-op patients would be bike based sprint’s, fast walking uphill, arm bike in the gym when they’re back open hopefully at some point, or maybe it was some sprint-based swimming where they do two lengths as fast as they can and rest after that.

We also have some people in the pool is doing aqua aerobics for working really hard for 30 seconds and relaxing for 30 seconds. So there are lots of different options out there for you to try and find that cardiovascular work that we may need.

So that brings me on to why is that important – keeping BMI, our body mass index and keeping your weight down after post-op is really important.

60 to 70% of people have been found to gain weight post hip replacement, and only 5% of people actually lose weight after a knee replacement.

It’s really important because within the replacement we can be incapacitated for a significant period – it’s really important that afterwards, we make sure that we’re conscious that we need to lose any weight that we may have gained pre-op or post up.

So, if we can make sure that after operations where we’re heading in the right direction we’re increasing our physical activity, we’re getting strong, we may be counting our calories to make sure we’re not eating too much because we’re not doing as much exercise – that would give us really positive effects.

If we can get the BMI down, or keep it the same throughout this period, it would be massively beneficial, but also adverse reactions postoperatively increase 35% if our weight is up towards maybe a quite heavier category – we really want to make sure that pre-op we are in a good place because that will minimize any chance of adverse reactions due to operation.

We can see here that this is lots of different graphs here. But what we can see is essentially on each of those individual graphs, if our BMI is higher – then our risk goes up. BMI is along the bottom of those small little graphs, and then the risk is on the left-hand side – you can look through yourselves and these slides will be around afterwards, for people to have a look at.

You can see that your risk does significantly increase if your BMI goes up, especially in the middle here of this table where you can see cardiovascular diseases, we can also see some of the cancers also not all, but some of them go up, especially our kidney cancer and other bits and pieces so it’s really important that we keep our BMI in a good place, or at least minimize it as best as we can, and really lead a fit healthy lifestyle there are so many positives to doing that.

Fit for life at SSC

So that’s what led us to start our Fit for Life – we had Fit for Life and we had done recently a Fit for Life, fit for golf campaign, and we also have our Fit for Life strength & conditioning programs – that’s to help people pre and post up to really try and improve their lifestyle, improve their wellness.

We offer sessions here that people come in for pre-op and post-op to really make sure they’re maximizing their strength, and really improving their fitness – we run that here for anybody who would be interested in, that’s something that we run here at the clinic or in the sports medicine building, and you can enquire using the email today as well.

Fitness Lab Target Sheet

But on that we’ve also created a fitness lab weekly guidance and targets that you can all download after this, you can stick up on the wall, or you can pop in the diary, and you can tick off when you get everything done and what you see there is 150 minutes of low-intensity exercise, or 75 minutes of moderate, or vigorous-intensity exercise, two strength sessions per week, a little bit of balance and mobility, so that could be Pilates, that could be yoga, even your golf could count as that, or tennis.

An 80/20 diet – what I mean by that is, if 80% of the time in our week, we are choosing the right decisions with our diet that allows us or affords us 20% of the time to go slightly off-piste – have that little bit of extra carrot cake maybe on the weekend, or something along those lines.

So, the 80/20 days a really good rule of thumb to use if we’re doing the right thing, every eight out of 10 meals, then two out of 10 meals a week or maybe choose something that’s a little bit off the script.

7000 steps, each and every day is a baseline, and then a little bit of extra protein with lunch or dinner – this helps support muscle strength.

This helps support muscle function and muscle growth, so if we’re doing our strength training, we’re looking to recover post-op and make sure our muscles are back into good quality – protein is essential.

And if we’re doing that through meat, cheeses and eggs that’s fine but if we’re doing that through vegetarian sources, we want to make sure that we’re mixing lots of different vegetables like beans with lentils to make sure we get the complete protein profile – that’s really important as well. We can go through that with anyone.

If you have any questions on that, please feel free to ask at the end, or if anyone’s really interested they can absolutely book an appointment with me and we can go through that and go through diet as well.

So thank you very much for listening. If you have any questions, I’ll be more than happy to answer them, or you can email [email protected].

We have health and fitness testing available to lots of people with VHI, Irish Life and Laya Healthcare.

We also offer it privately as well if you’d be interested and a lot of people have been availing of that recently.

With our MCL, we want to make sure that the quadriceps and hamstring muscles are as strong as possible after the injury.

Often we will see some waste away of those muscles and we can see some weakness after the injury, so it is really important that you get those back to full strength after the injury, but also looking at the hip strength, so with medial collateral ligament on the inside of the knee, we have got to make sure the hip strength is really as strong as it can be to try and prevent that inwards motion of the knee which causes some of that strain the MCL. So if the legs are equally as strong as each other, so the non-injured side is equally as strong as the injured side, and the hip strength is equally strong, then that is probably our markers to head back onto the pitch as well. But she has to make sure that we are as strong in the quads and the hamstrings to really help protect that MCL going forward.

After a year there should not really be any contraindications on the MCL – again, I presume that’s noted by potentially a surgeon or the sports physician but otherwise, just making sure the muscles are as strong as possible would be the best guidance.

It is great to keep up the heart rate, trampolining is a fantastic exercise for that side of things for sure. It can also help with lower limb strength, there is some evidence there as well.

It wouldn’t be the only exercise I would do, but absolutely you could use that to increase the heart rate and to strengthen the lower limb.You may still want to add a few more exercises on top, but I think it is a fantastic exercise and a lot of people find it is great fun.

Often if we have a good range of motion but we don’t necessarily have the full strength back in the hip – that is when we will see the limp kind of occur.Making sure that the side of the hip muscles are really strong because they are the ones that are often cut through, so you want to make sure that the side of the hip muscles are really strong to provide stability to that hip so that you can prevent that limp.

Also making sure that you do some gait re-education training. Our physios at the clinic will do a lot to make sure your gait cycle is back to normal. Often the limp can be a learnt pattern, so it’s making sure that we train that gait pattern. We often focus on picking the knees up, making sure you almost do a mini marching pattern to retrain the gait, so the muscles need to be strong first because no amount of gait retraining will retrain the muscles if they are not strong, but then afterwards we can do some gait re-training where we focus on lifting the knees up a little bit higher to try and prevent that limp.

So with the rotator cuff, it kind of activates in any of our shoulder strengthening exercises, so any kind of pressing movement overhead, especially will make sure the rotator cuff’s doing some work. If we are limited in terms of the range of motion and that is where we might be some of our banded rotator cuff exercises, so anything where the upper body is rotating – so in these sorts plains through here would definitely help. On that one I would definitely speak to a physio, to try and get specific rotator cuff exercises because the rotator cuff is a fairly large component to the shoulder.

You could work rotator cuff exercises for the front of the shoulder and the back of the shoulder and both would have completely different effects. So a little bit of specificity is required, and that is where you might get some help from a physio, but any kind of pressing movements overhead if you can are fantastic for strengthening rotator cuff, any ones where your arms are moving out to the side like a lateral raise can also be very good.

But there are also some specific banded ones we’d want to look at, especially if you have had surgery before, there might be some specific deficits after that surgery, so we want to make sure that they are kind of tidied up, so that would be my answer there.

So we want to make sure that the back of our Glute muscles are very strong, so hip bridges are fantastic for building strength in the backside muscles. With the side of the hip muscles as well, you want to focus on laying on the side and lifting the leg up to the side of the hip muscles to get some good strengthening as well.

An exercise such as a step up on the bottom step of the stairs would also really help to strengthen the hip muscles as well. These are three easy ones that you can do at home. They will also help with the flexibility – we would really recommend getting strong. The surgery will help some of the flexibility as well, but really getting stronger in those muscles is the biggest priority prior to going into the surgery because they are the muscles you’re going to lose the quickest, so if we can get them strong pre-surgery, they will get stronger, easier and better after the surgery as well and that is probably one of the most important points – if we don’t have it before the surgery it’s going to be really hard for us to get it after the surgery.

Generally we would say about 20 minutes. If we are doing high intensity and really pushing, we won’t be able to do longer than you know 15-20 minutes, so just how comfortable you feel pushing high-intensity kind of conditioning, so usually we would say you know if we’re doing 10 to 20 intervals roughly taking a minute per interval, that would be perfect, but it just depends on what exercise and how you’re doing – so something like a rower might be slightly longer, whereas if we’re doing a lot of bike work it might be a little bit shorter intensity.

So generally around about 15 to 20 minutes is more than enough to get the high intensity so it is really time efficient and you just obviously push yourself quite hard when you’re working and then the rest of it is really relaxed – that should be perfect for most people.

It’s hard to tell – I mean if there is a specific range of motion that you will always find is giving way, then that is definitely something to investigate a little bit further, because that shouldn’t be happening. Especially if you are getting pain first then giving way. The giving way there would most likely be due to the pain so we need to find out the root cause is that is causing the pain. Is there a pathology in the hip that we maybe need to MRI or look at and assess? Especially if it is always the exact same movement. That is when I am definitely getting to see maybe one of the sports doctors or a physio to have a look at that.

If it is completely different movements, then I think that could be a weakness. But if it is always the same movements if it’s always rotations or always in the same movement pattern then definitely I would get that looked at, just because we would want to see why that is the case.

There are Zoom classes on going – a lot of places are still doing zoom classes. So that is definitely something to look at because staying accountable is really important during this period. Either having a buddy who you do the exercises with, who make sure you do them at a specific time, and don’t slack off – I think is really important. Finding a class where you can sign up and book in and that just holds you accountable – that is definitely one part because it’s too, especially during lockdown, to forget about exercise and after a tiring day, it’s very easy.

So either having a partner that you do the exercise with where you meet up on zoom is a really good idea. Secondly to that let’s have a look at some of the zoom classes because they are excellent as well and then it’s just a case of trying to make it a habit and make it something you do in your week without even thinking, you already have that timeboxed off and go and make it as easy as possible. That’s where doing exercise earlier in the day is often better because as you get through the day you have more mental fatigue and you’ll be more likely to find the excuses, so if you can do it early in the day before you start your working day that’s generally one of the best bits of advice we can give if you struggle with that motivation

Try and take away any of the kind of resistance of the day before we have a million and one things to do. That is generally a good one but look at the classes on zoom, they are really good and lots of people have been very imaginative with the ways that they are going about them now.

With this one, we want to make sure those quadriceps muscles are as strong as possible, so squatting to a height that you can do without pain is really good, making sure that we do an exercise called a straight leg raise because that shouldn’t cause your knee any pain at all and you can look that one up online and that is very easy to do.

Those two are two key ones that are quite comfortable. Also, we’d often use the wall hold. You’ll have seen it on the TV recently in Ireland’s fittest families, but just adjusting it for yourself where you can do it without any pain is really important. If you can use a bike or even one of the small bikes that you can get, that just go on the floor to keep the knee moving is really important as well so if you can get strengthening into the leg, those would be the four ones that I would go for at the moment and you don’t need any real equipment apart from the small bike that you can buy online. I think we have them at the clinic as well that you can get in there – those four would be my key four without a gym at the moment.

To make an appointment with Luke or to learn more about FitnessLab please email [email protected] or call 01 5262050
shutterstock 1467689543

‘5 Common Questions Patients Ask About Hip Replacements‘ with Professor Joe Queally

In this video, Professor Joe Queally, Consultant Orthopaedic Surgeon specialising in hip and knee pain discusses the 5 most common questions he is asked about hip replacements.

Joseph Queally Profile Web1Professor Joe Queally is a Consultant Orthopaedic Surgeon at UPMC Sports Surgery Clinic in Santry Dublin who specialises in the hip and knee.

Good evening, everyone. Joe Queally here, one of the Orthopaedic Consultants at the UPMC Sports Surgery Clinic. I’m also an associate professor at Trinity College Dublin. My talk this evening is five common questions that patients ask me about hip replacements. The idea is that I will try and give you answers based on the most recent evidence and scientific literature that’s available.

Asking questions about hip replacements, in general – it’s important to ask your surgeon whoever he or she may be as to how successful it is. And these are questions that would include how long would it last? What type of hip replacement is being used? Questions that are particularly relevant to your personal situation – what do you want to be able to do after the hip replacement? Also, to take into account what medical problems you might have, such as having diabetes or being overweight, how this might affect your hip replacement, and what you can do to help optimize and make sure that you have the best outcome possible. It is good to have answers that are based on the most up to date, available evidence as possible, because in medicine facts and evidence, change all the time and it’s important to have the most accurate and up to date information when you’re when you’re making a decision about going ahead with a total hip replacement.

Before we get into these questions I’m just going to, in a very simple way, discuss how we measure success after a total hip replacement. There are two basic ways that we measure success: the first we look at is implant survivorship – by that I mean is, how long does the joint replacement last. That’s really important because you want your hip replacement to last for as long as possible. The second question that we look at is how well does your hip replacement work. So we want it to last really long, and we want it to work really well. In terms of how well it works, we’re interested in, particularly how quickly patients can get back to function – to walking into doing things that they would like to do. We’re also interested in seeing how long this good function lasts. We would hope that your input, along with lasting a long time, would also work very well for a long time. When we’re deciding what type of hip replacement to use and how to put it in. These are the two basic questions that we look at.

So, how do we gather evidence on Hip Replacements? There are a few basic ways that we can gather evidence. The first is that surgeons record how well their patients did. They publish their work in an academic paper and a simple example of this is a surgeon might say I did 50 hip replacements – I asked him questions about how well they’re recovered and I found that they could all walk without crutches, by eight weeks after their surgery. This generally limits the amount of patients to relatively smaller numbers.

The second way that we can try and figure out which is the best type of hip replacement, or the best type of technique is we can compare two different treatments. So, a surgeon can set up a study where he does, or she does 25 replacements using one technique, and then does 25 hip replacements, compared to a different technique, and they can say that the ‘x’ technique resulted in a better hip replacement, because it lasted for 10 years longer than the ‘y’ hip replacement.

The third way we have of looking at how well joint replacements do in general and this is becoming more common, is that in most countries all surgeons have to report on how well their patients did to a national body, so you have to submit data, saying what type of hip replacement that you have done, and the data is subsequently gathered on how long your hip replacements last, and how well they work. This is a really powerful tool, because it gathers information on hundreds of thousands of hip replacements, over prolonged periods of time and it gives really good evidence on which replacements work best and as care and techniques evolve, which techniques are better than others.

So that’s just a backdrop for how we figure out how joint replacements work well. When I’m answering the five most common questions, this is the type of evidence studies that I will be discussing.

So the first question and the most obvious question is what is a hip replacement?

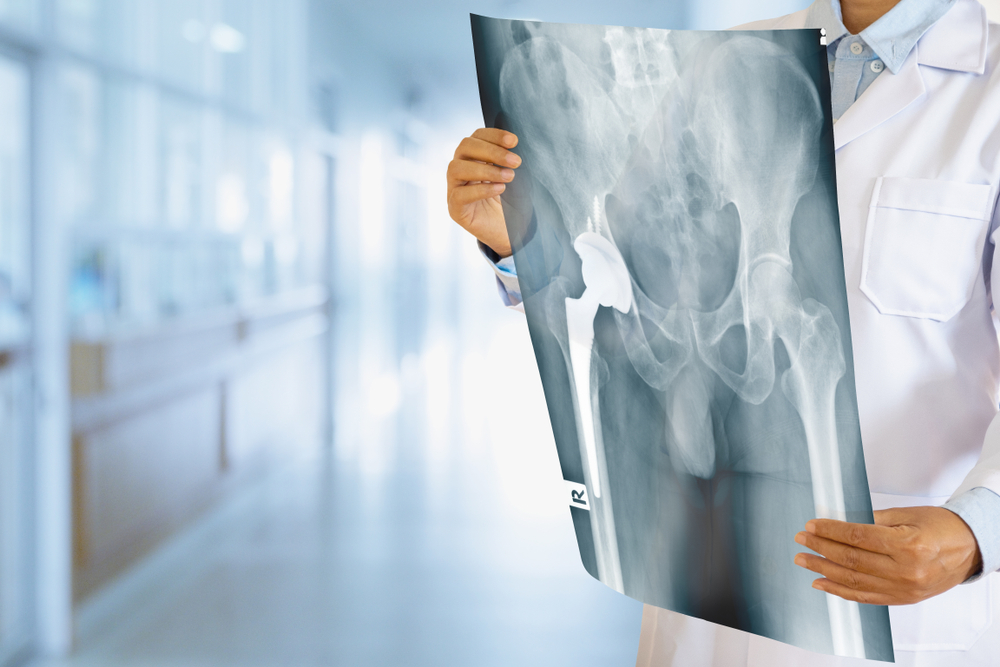
A hip replacement is where somebody’s hip joint, which is this circle here, is removed in its entirety, due to a problem with it. and an implant which we can see here on the right is put in its place. The implant mimics your natural hip and that it’s a ball and socket type of implant. So the socket part here goes into the pelvis and into the thigh bone here, there is a stem with a bald part attached. The actual joint then is this ball and socket baring here, which the idea is that it mimics your own native hip joint. So, When do we do it?  The most common reason for doing hip replacement is for arthritis of the hip.

What is arthritis?

So a normal hip joint, as we can see here on the left, the ball and socket part of the joint is lined with cartilage which is a very smooth structure that allows your joints to move like a bearing and it allows it to move in a smooth and friction-free way. What happens with arthritis is that this cartilage lining gets worn out, or gets destroyed for a variety of different reasons. Because of that, your hip joint is no longer able to move in a smooth and pain-free way. What happens after a while is that bone starts to grind on bone. This causes severe hip pain and consequent reduced ability to walk or to do things like, play golf, gardening, or hiking. So really osteoarthritis is damaged cartilage around the lining of both the ball and the socket part of the hip joint.

This is an example here on an X-ray of a normal hip, over here on the left side. We can see space between the ball and socket part of the hip joint. This is where the cartilage sits, which I’ve just mentioned earlier. When we look at the right here there’s no space between the bones. This is because the cartilage has been damaged or worn away. What’s happening here on the right side is that bone is grinding on bone. It’s a bit like a rusty hinge – it doesn’t move in a smooth manner, it causes pain, because of that patients can’t walk properly, and they can’t do activities, such as, as I said, such as such as playing golf or even dressing themselves, or even getting in and out of a car can be difficult. This is a patient who has had arthritis in both hips. He’s had both hips replaced as we can see here.

So the second question that I get asked quite commonly is how long would my hip replacement last?

Again this is a really important question because we want hip replacements to last for as long as possible. Because sometimes we need to do hip replacements a second time around, and that’s called a revision hip replacement. Revision hip replacements are a harder operation both for patients to recover from and also for the surgeon to carry out. They are best avoided for as long as possible. That’s why we tend to avoid doing hip replacements in younger patients because we want to avoid having to do a second hip replacement, and some patients they need three and four and in very rare cases even up to five hip replacements over a prolonged period.

How long can we say that hip replacements last in general?

This is a paper published in 2019 in The Lancet, which is one of the leading medical journals – the author’s looked at a huge number of hip replacements that were reported in the scientific literature – so they looked at all surgeons who reported how other hip replacements were doing, and they also looked at joint registries in countries such as the UK, New Zealand, Australia and the Scandinavian countries, who have been recording all hip replacements that are done in their countries and how long they last.

They added all the hips together to try and come up with a figure of how long does the average hip replacement last for. The number of hips that they included in the study was 228,888 hips, which is a huge number. This is really good because the more numbers in a study, the more accurate the data is.

So what did they find?

They found that 85% of patients can expect for hip replacements last 15 years, 75% of patients can expect for hip replacements last 20 years, and 58% of patients can expect her hip replacements to last 25 years.

So roughly over half of patients who have a hip replacement can expect it to last 25 years which is a good outcome – this says these figures have slowly improved over the past 30 to 40 years. Obviously the other side to this is 40% of patients, their hip replacement won’t last 25 years, and these patients often need to have their hip replacement done a second time, which is called a revision hip replacement. The average age at which patients in the study have a hip replacement is 67. The majority were women at 55%, and the vast majority of hip replacements were carried out for osteoarthritis.

Other causes for hip replacements apart from arthritis, will be for patients who have damaged their hip really badly after an accident who have a really bad hip fracture, patients who have had infections in their hip which is unusual but sometimes happens, or patients who have had childhood hip disease – who have had an issue with their hips since birth, where their hips haven’t quite formed properly.

Another question I get asked all the time in my clinic is which surgical approach is best?

By which surgical approach I mean is – what is the best way to put in a hip replacement, and the best way to get in and around the muscles to put the replacement in?

There is three basic ways to do this:

One is the anterior approach – this is where the hip replacement is put in from the front of your hip. There is what’s called the anterolateral approach, where the hip replacement is put in from the side. And then there is the posterior approach, where the hip replacement is put in from the back of your hip, and they are the three main ways that we put hip replacements in at the minute. Patients often ask which is which of these three is the best way to do it?

The posterior approach, which is the approach that I use, is the most commonly used and this is where the hip replacement is put in via dissection through the muscles of the back of the hip. This is a good approach because it gives you a very good view of the hip joint itself and it allows the hip replacement to be put in a really good position. There’s a theoretical disadvantage that there might be a higher risk of dislocation.

The second approach is anterolateral – this is where the hip is put in from the side. This involves going through muscles at the side of the hip, and the potential disadvantage of this is that there may be a slight risk of limp after this approach, due to disrupting the muscles at the side of your hip

The third approach is the anterior approach which is a newer approach, where the hip replacement is put in from the front of the hip. Muscle sparing means that instead of cutting through muscles, the hip replacement is put in between muscles. The assumed advantage of this is that you may get back quicker to doing activities such as walking. The disadvantage of this is that there might be a slight increased risk of problems afterwards, such as fracture when putting the hip replacement in, or injuring nerves at the front of your hip.

Obviously, for surgeons and for patients, we all want to know which of these three approaches is the best and which one should I have for my particular situation. The answer needs to be found in the evidence and what studies show to be the difference between the three approaches. I just picked one very recent paper which was published in June last year, which has come from Boston and Copenhagen. These surgeons looked at 93 patients in two different groups. In one patient they use the anterior approach and in the 2nd 93 patients to use the posterior approach. What they looked at was how well do the hip replacements function from six weeks, up to to five years. They are wondering which approach – the anterior approach from the front or the posterior approach from the back, results in the best hip function from very early on to, to the five year mark. They found that both approaches resulted in a significant improvement in function by asking patients questions such as, how far can you walk? What activities of daily living can you do? They found that there was no difference between the two approaches in scores at six weeks, one year or five year. They found for hip function it doesn’t really matter which approach is used. There is no difference.

The next paper I’m going to look at is, as I mentioned at the beginning, is how long does a hip replacement last when it’s done via the anterior, from the front, from the side or from the back? This is a study from one of the Scandinavian registries, and they looked at over 20,000 patients that had each of these three approaches either again from the front, from the side, or from the back. They looked at the implant survival as two and five years. They found no difference between the approaches in terms of survivorship (98% at five years). They concluded that how long a hip replacement lasts is not linked to which approach is used.

So in terms of which approach to recommend to patients: The scientific evidence does not show benefit of one approach over another, in terms of how long the implant lasts, how well it works, or how quick the patients have returned to walking. So even though I use the posterior approach, because it’s the approach that I have been trained in but I can’t say that that’s any better than the other two approaches, and vice versa.

So, moving on to question number four, this is ‘what about hip resurfacing instead of hip replacement?’

So what is hip resurfacing? It is a form of hip replacement where instead of taking you out to hold the hip joint as we see here on the right -much of the hip joint, particularly the ball part of the hip joint is retained, and the metal cap is put on the top of the ball part.

So what it means is that just less of your hip joint removed and the potential advantages to this are that it kind of preserves more of your natural hip joint. So in theory could result, potentially in better hip movements and better hip function. It’s also less likely to dislocate and this is due to the size of the cap that is put on the top of the ball part. The big problem with this metal cap was that the baring that was being used was metal on metal and this led to big problems with metal ions. Most hip replacements have a metal on plastic baring or ceramic on plastic bearing which we’ll see in a minute. But this resurfacing type of hip replacement has to use a metal on metal bearing. As a lot of people are probably aware, this caused major problems with early failure of a lot of patients who had hip resurfacing.

This was due to a problem called metallosis. Here on the left we see what a standard hip replacement bearing is like, whether it’s a metal head and a plastic liner in the socket. With resurfacing, there is a metal cap and a metal liner in the socket. This resulted in the production of metal debris or wear in the hip joint, and this is demonstrated here in this black material, and it resulted in early failure of hip replacements, but up to 25% of hip replacements failing at the five-year mark, when this should be 6%.

This resulted in a product recall, where all these procedures were stopped, and all the previous resurfacing had to be investigated and some of them had to be replaced and because that hip resurfacing essentially died out and become a procedure that was no longer performed. Until, 2019, when Andy Murray, a tennis player famously had a Birmingham, which is a type of hip resurfacing procedure, carried out. It has started to reappear in a very small subgroup or selection of patients. There is an argument that there may be a role again now for resurfacing in some patients, there may be better implants where this metal wear is less likely to happen, and it may be better for younger patients who are young and active and want to continue to have a very active sporting life in particular.

So again, the rules are the same, we have to look at what is the evidence say as to whether hip resurfacing is a good idea or not. In terms of how long they last – they last about 94% for 10 years which is similar to a total hip replacement, and what about how well they work this is a paper published in the BMJ which is another major medical journal. In 2018, they looked at 60 patients who had hip resurfacing and 62 patients who had a standard total hip replacement. They found no difference in function at any stage, from six weeks to five years.

So where are we with hip resurfacing in 2020? Is there a role for younger patients who are active, maybe patients who are aged 30 to 50? Is there improved implant technology where this metal wear effect is less?

I would say for most patients, there is no evidence to support this currently. Hip resurfacing is generally to be avoided due to potential serious complications, as there’s no evidence at this current moment in time that these patients do any better than total hip replacement, in terms of how long it lasts, or how well it works.

So question number five is should I have a hip replacement if I am overweight or what does being overweight mean for me in terms of my hip replacement?

This is a study again another big study published in 2020. It looks at how being overweight affect having your hip replacement. They divided patients up into three different groups based on their body mass index which is a measure of how overweight or obese you are based on your weight and your height.

For patients with a BMI less than 30 were considered non-obese – greater than 30 they were considered obese and a BMI greater than 40 they were considered morbidly obese. This study is a great study because it looked at over 2 million patients, and looked at their outcomes after having a total hip replacement. They found that being overweight and having hip replacement resulted in a slightly increased risk of complications or problems after your hip replacements.

These figures here represent how many times more likely you are to have a problem – so for infection, which can be a big problem in hip replacement surgery or any joint replacement surgery, if you were obese to the point your BMI is over 30 – you’re 2.7 times more likely to have a problem with infection afterwards. If you are morbidly obese, where the BMI is greater than 40 that rises to 3.69 times more likely to have a problem with infection. In real terms, this changes maybe from about .5% to 1.5 or 2% of patients who have a hip replacement, but it is a significant number, and it is something that patients need to be aware of.  There is also slightly higher increased risk of dislocation and the need for having to have a second hip replacement.

So what does it mean being overweight and being significantly overweight does increase your risk of complication after total hip replacement. I don’t think it means that you can’t have a hip replacement, but it means for patients who are who are significantly overweight should consider a trial of weight loss or weight reduction to try and reduce and minimise the risk of having a problem after your hip replacement prior to having it. It is important that patients are aware of the risks and that you are given an opportunity and help to lose weight, and to drop your BMI before  surgery.

Just to summarise the talk, hip replacement involves replacing your hip joint with an implant to restore pain-free movement back into your hip and with that comes an improvement in your quality of life. In terms of how long hip replacements last?  Over half of patients can expect your hip replacement to last 25 years.

In terms of how hip replacements are put in?  there’s no evidence to support one approach over the other at this moment in time. For hip resurfacing, there is no role or minimal role for hip resurfacing at this current time, and being overweight increases the risk of complications slightly, and it’s best to try and reduce your weight prior to surgery.

Given your age impingement is a common enough problem these days, and it can lead to arthritis or degeneration of your hip cartilage.

Really, many impingement patients or patients who want to live without arthritis do need a hip replacement. When you need a hip replacement really is decided by the severity of your symptoms. So when your symptoms are severe to the point where you have constant pain, where you can’t walk a reasonable distance or do the activities of daily living that you like to do, such as walking for example or playing golf and you are having difficulty sleeping at night – they are the general criteria for proceeding with a hip replacement.

Often we try and delay a hip replacement for patients who have lesser symptoms and a hip steroid injection is something that can be useful. The reason for that is the average life span of a hip replacement for about 60% of patients now is about 20 years. You may need a second hip replacement after that, and a steroid injection is used for patients with lesser symptoms, to try and delay a hip replacement. But there will come a time I’m sure when you may well need a hip replacement, and if the steroid injection doesn’t have much effect or starts to wear off, then that is generally the indicators that it’s time for a hip replacement.

Yes, that’s a great question. I guess the best answer to that is maybe. There’s no reason why you can’t go horse riding. It depends on factors such as what your hip flexibility is like after your hip replacement, and that in turn will depend on your hip flexibility before your hip replacement.

So some patients have really stiff, hips before surgery due to arthritis. Whilst a hip replacement will bring back some flexibility in your hip, and may not bring back enough flexibility for horse riding and for getting on a horse and using a saddle. You can certainly use aids to get onto the horse, like a stamp box. But spreading your knee’s on the saddle is the difficult part, it certainly is possible but you know, it depends on what your flexibility of muscles is like after your hip replacement.

I would say I have a written a recent article that you can access on my website for anybody who’s asked questions about what can you do when after a hip replacement? My website is www.joequealy.com. On the news section, there is an article that goes through most sports – it’s based on a recent paper published in one of the leading national hip journals, and when it’s safe to go back to activities such as golf, cycling, even tennis, running and horse riding. For horse riding, it’s generally at the six-month mark, if you have enough flexibility and range of movement after your surgery.

Yeah again so golf, you can generally get back to Golf a little earlier. So generally I will say at the 12-week mark – some patients can get back a little earlier than that and again, your return to function after hip surgery – many things influence it, like what your flexibility is like after your hip replacement, which as I said, is influenced by your flexibility beforehand, your overall muscle strength and coordination will decide what type of activities you can do afterwards.

Again this feeds into the point I made there about not leaving it too late to get a hip replacement you know, if you wait until symptoms are very severe, which we sometimes see, then it’s hard to get good hip flexibility afterwards even with a hip replacement, that can limit your ability to return to any kind of higher functioning activity such as golf and so on.

The most common anaesthetic by far is a spinal or epidural anaesthetic, which I would say in my practice is carried out for probably 96% of patients. This is really because it is the safest form of anesthesia for the majority of patients.

So the benefits to it are that it’s safer, as it protects your heart and lungs from having a general anaesthetic. It also allows you to recover a bit quicker afterwards. Most of our hip replacement programs are now enhanced recovery, or fast-tracked hip replacement, where we aim to get people or patients walking, ideally within four to six hours of other hip replacements – so the same day of surgery typically in the afternoon. We can do this because we use spinal or epidural anaesthesia that wears off. It is designed to wear off quickly. It’s designed to get patients walking and mobilising as soon as possible which will speed up and enhance your recovery in general.

Again, this comes down to your range of movement of your hip is a function of two things really – one is your flexibility and the second is your muscle strength around your hip, and how much range of movement you have after your hip replacement is dependent to some degree on how flexible your hip was beforehand, as I’ve mentioned.

So if you’ve had good flexibility before your hip replacement, good muscle strength, and you’re quite active as you seem to be, then I would expect a good range of movement afterwards, whether you get up to 120 degrees of hip flexion, that’s hard to guarantee. They certainly would expect a good enough range of movement to do you know most things such as cycling and swimming, and even playing tennis is possible, again after about six months after a hip replacement.

Yeah, so pain after a hip replacement does happen sometimes. The satisfaction rate from the scientific literature after a hip replacement is about somewhere between 90 to 95%.

So for most patients – it is probably the most successful operation of all time really, in terms of satisfaction after surgery, but the corollary of that is there is 5% of patients who have problems or difficulties. That is due to a variety of different reasons.One of the more common causes of pain after hip replacement is bursitis on the outside of your hip, and it often causes pain on the outside of your hip. This is generally treatable with, generally with anti-inflammatories and physiotherapy to stretch the hip abductor muscles in that area in your hip – sometimes for your hip, a steroid injection into the bursa is required.

So in general for most patients, bursitis is generally treatable, but there are some patients who do have ongoing difficulties, I have to say. Does it mean that it would happen if you had another hip replacement? I would say not necessarily, but again, it would be hard to guarantee that it wouldn’t happen. But yes that’s bursitis after hip replacement.

So it’s a good question, and again, it’s, you know, as I said, timing and hip replacement – it’s about getting the timing right really. Those general triggers that I mentioned about having constant pain, pain at night time, and the inability to walk a reasonable distance. They’re generally the triggers that we use to proceed with the hip replacement.

Some patients may you know, for whatever reason, may have those symptoms for many years. And maybe avoiding surgery or they may not be aware of surgery or they may not be aware of the diagnosis, and often they’ve very stiff hips and recovery afterwards is not as good as if they had more flexible hips, before surgery. So certainly about getting the timing right – not waiting too long with severe symptoms, to try and optimise and get the best possible outcome after your hip replacement, as I said though, going too early is also a bad idea.  It’s about getting the timing right but for most patients that I meet, most patients do generally have a good sense of the right timing for their hip replacement.

To make an appointment with Professor Queally please call 01 5262140 or email [email protected]

A letter of referral may be required.

Fitness Programme for Golf

Total Tee Box Warm Up with Luke Hart.

This is the total tee box warm up. This is 5exercises that you can do when you are running late to the tee box to make sure you maximise your performance on the first hole:

So the first exercise we are going to do is some stick rotations. So first off take your 5 iron/driver and pop it in the crease of the arms. You are going to have some soft knees – just bend the knees as you would address the golf ball, and all we are going to do is rotate down to the foot, and back through.

We should have a small bend in the knees.

You should see that one knee flexes and one knee stays a little bit straighter.

From the side – push the bum back, rotate, and back up, rotate and back up.

You are going to do 2 lots of 10.

So this one is to warm up our legs – this is really important especially if you suffer from any kind of knee pain, it is really important we make sure to warm up those muscles before we go onto the course, but also to make sure we develop power in our swing.

What we are going to do is take one leg forwards, one leg backwards, and hold your club in the opposite hand. All we are going to do is dip down and back up again – just small little mini-split squats using the club just to help you.

We want to make sure the knee doesn’t come over the toe. 2 lots of 5 on each leg – literally 2 minutes.

If you find the split squat one a little bit hard I have got one other for you: So you are going to pop the club in the hands and all we are going to do is a mini little squat.

So we are going to dip, and drive, dip and drive – just to get those legs warm, again pushing the bum backwards, not letting the knees go over the toes.

Again 2 sets of 5.

So this one is now a stretch for your upper body.

What we are going to do is pop the arm across the body, put the hand across – all we are going to do is as we go through there we are just going to rotate around, using the opposite arm to pull you around, hold for a couple of seconds (you should feel this all in your upper back), and relax off.

Then across the other side – pull across and rotate across, hold for a couple of seconds, and relax off.

You can do that twice on each side just once and then move onto your next exercise.

For this last one now, we are going to incrementally increase the speed. We are going to use our five-iron because it is the heaviest club in the bag.

We are going to set up into our swing and we are going to go 3 slow, 3 medium and 3 fast.

You are just going to try to go as fast as you can on the last three before then you take out the club you are going to use on this hole.

So three easy.

Three medium now.

Then three fast to get you nice and warmed up.

That is your warm-up finished – settle yourself down, take the right club and move onto the first tee.

To make an appointment with a member of the Sports Medicine team at UPMC Sports Surgery Clinic, call 01 526 2030 or email [email protected]